
September 30th, 2026 | 20 min. read

IVF success rates are highest with younger eggs and decline as egg age increases, especially after age 40. Ovarian response, sperm health, embryo development, diagnosis, and treatment history also affect outcomes. National averages show broad trends, but a fertility specialist can help estimate your individual chances based on your testing, history, and goals.
At a glance
- → The age of the eggs at retrieval is one of the strongest predictors of IVF success when using your own eggs.
- → Success rates measured per embryo transfer are often higher than rates measured per egg retrieval. They exclude cycles that never reached the transfer stage.
- → AMH helps predict ovarian response to medication. It does not show whether an individual egg is chromosomally healthy.
- → With donor eggs, the donor’s age at retrieval has a stronger effect on embryo potential than the age of the person carrying the pregnancy.
- → Find Illume Fertility’s latest finalized SART results and national comparisons on our IVF Success Rates page.
IVF Success Across Age Groups
National IVF success rates are grouped by age at egg retrieval, not age at embryo transfer. That distinction matters since embryo potential is tied more closely to the age of the eggs when they were retrieved. SART identifies age at egg retrieval as a major predictor of IVF success.
Embryos created from younger eggs retain the age-related reproductive potential associated with those eggs, even when transferred years later.
For example, if you undergo IVF at age 32, create embryos, and freeze them for future use, their age-related reproductive potential reflects the age of the eggs at retrieval. If you transfer one of those embryos at age 38, it was still created from a 32-year-old egg.
Note: Your age at the time of embryo transfer and pregnancy still matters for pregnancy-related health risks, even when the embryo was created from younger eggs.
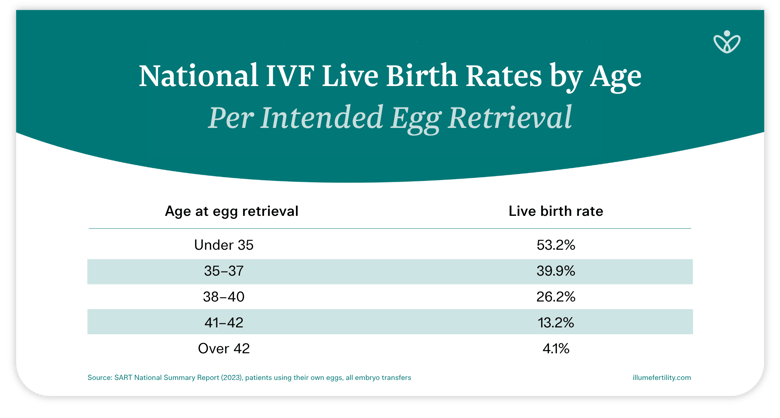
How Age at Egg Freezing Affects IVF Outcomes
Freezing eggs at a younger age preserves that age-related advantage too, but there is more uncertainty. Until those eggs are thawed and fertilized, you won't know how many will survive the thaw, fertilize normally, and develop into usable embryos.
Age at egg freezing and the number of eggs frozen both affect future success. With frozen embryos, you already know which eggs successfully fertilized and developed to the stage at which they were frozen.
Why IVF Success Rates Vary
Two IVF statistics can look contradictory when they measure different points in treatment. Before comparing percentages, always check the outcome being measured and which types of cycles are included in the calculation.
When you review outcome reports from the Society for Assisted Reproduction (SART), there are a few common terms you will encounter. Here's what to know before you dive in:
Live Birth Rate
The percentage of patients, egg retrievals, treatment cycles, or embryo transfers that result in a live birth. It differs from a positive pregnancy test or clinical pregnancy rate, since not every pregnancy progresses to delivery.
Clinical Pregnancy Rate
The percentage of cycles or transfers that result in a pregnancy confirmed by ultrasound. Clinical pregnancy rates are often higher than live birth rates, since pregnancy loss can occur after the first ultrasound.
Per Intended Egg Retrieval
This begins with cycles started with the intention of retrieving eggs. It includes cycles canceled before retrieval, retrievals that yield no eggs, and cycles that never reach embryo transfer.
Per Actual Egg Retrieval
This begins with cycles in which an egg retrieval actually takes place, including retrievals that yield no eggs. It excludes cycles canceled before retrieval.
Per Embryo Transfer
This measures outcomes among embryo transfers performed. It excludes cycles that did not reach transfer, so the reported rate is often higher than a rate calculated per retrieval.
Cumulative Live Birth Rate
This estimates the chance of at least one live birth across multiple transfers from a retrieval, or across multiple treatment cycles, depending on the report. Check the time frame and how the report defines a cycle before comparing cumulative rates.
CDC's guide to interpreting ART success rates explains these measures in greater detail and cautions against comparing percentages that use different denominators.
Comparing Fertility Clinics
A clinic with a high IVF success rate isn't automatically the right choice for every patient. Practices treat different patient populations, specialize in different diagnoses, and may use different criteria when deciding whether treatment is medically appropriate.
One clinic may treat patients with a very low predicted chance of success. Another may recommend donor eggs or decline treatment in similar circumstances. Small patient numbers can also make one age group appear unusually high or low in a given reporting year.
Consider these factors alongside a clinic's published success rates:
- The characteristics and diagnoses of the patients included in the data
- The number of cycles performed in each age group
- Whether outcomes are reported per retrieval, transfer, or patient
- Whether the clinic accepts complex or poor-prognosis cases
- Laboratory accreditation, quality controls, and embryology expertise
- Available treatment options and willingness to individualize care
- Transparency about risks, limitations, and realistic expectations
- The quality of communication and support throughout treatment
The CDC cautions that direct comparisons of clinic success rates can be misleading.
Rather than choosing a clinic based on one impressive number, look for transparent reporting, sufficient cycle volume, an experienced laboratory, and a team willing to explain how its published patient population compares with your circumstances.
What Impacts IVF Success the Most
No single data point can fully predict your IVF outcome. At Illume Fertility, your reproductive endocrinologist will always consider several factors together and use what is learned during treatment to adjust your plan and optimize your chances of success.
1. Age of the Eggs
Age at egg retrieval is one of the strongest predictors of success when using your own eggs.
As eggs age, they become more likely to have an abnormal number of chromosomes, called aneuploidy. An aneuploid embryo is less likely to implant and more likely to result in pregnancy loss. Some chromosome abnormalities can result in a chromosomal condition.
Donor Eggs and the Role of Age
When donor eggs or donor embryos are used, the age of the person who provided the egg at retrieval affects embryo potential more than the age of the person carrying the pregnancy.
For this reason, the CDC does not divide donor egg and donor embryo success rates by the age of the person receiving the embryo. The age and health of the person carrying the pregnancy still matter when assessing pregnancy-related risks and determining whether it is medically safe to proceed.
Age & Fertility Explained
In this episode of Ask Monica, Illume's Nurse Practitioner Monica Moore explores how age affects your fertility and the role it can play in IVF outcomes.

2. Embryo Development & Chromosomal Health
An embryo must fertilize normally, continue developing in the laboratory, and reach a stage suitable for transfer or freezing. Its developmental stage, appearance, chromosomal status, and ability to tolerate freezing and thawing can all influence its reproductive potential.
Embryo grading provides useful information about appearance and development, but it cannot confirm chromosomal health. An embryo with a high grade may be aneuploid. An embryo with a lower grade may be chromosomally normal and result in a live birth.
3. Ovarian Reserve & Response to Medication
Ovarian reserve testing helps estimate how many eggs may be retrieved and how strongly the ovaries are likely to respond to stimulation. Your physician may consider anti-Müllerian hormone (AMH), antral follicle count, cycle day 3 FSH and estradiol, and any previous response to fertility medication.
These markers are valuable for planning an IVF protocol and anticipating egg yield, but they do not directly measure egg quality or determine whether pregnancy is possible.
ASRM’s guidance on ovarian reserve notes that AMH and antral follicle count are far better at predicting ovarian response than pregnancy or live birth.
4. Sperm Health
Sperm contribute half of an embryo’s genetic material. A male fertility evaluation can identify factors that affect treatment when sperm from a partner or known donor are being used. A semen analysis evaluates concentration, motility, morphology, semen volume, and total motile sperm (TMS) count.
One abnormal result may need to be repeated because semen parameters can vary. The full pattern helps determine whether IUI remains reasonable, whether IVF is more appropriate, or whether intracytoplasmic sperm injection (ICSI) should be considered.
A semen analysis cannot measure every aspect of sperm function, and no individual parameter perfectly predicts pregnancy. The AUA/ASRM male infertility guideline recommends interpreting the results together and within the broader fertility evaluation.
5. Infertility Diagnosis
The reason you need fertility treatment can affect both the recommended path and the likelihood of success.
Relevant diagnoses include diminished ovarian reserve, blocked fallopian tubes, endometriosis, PMOS (formerly PCOS), ovulatory disorders, male factor infertility, recurrent pregnancy loss, genetic conditions, and unexplained infertility.
6. Uterine Factors
The uterine environment matters, too. Ultrasound, sonohysterogram (SHG), hysterosalpingogram (HSG), or hysteroscopy may be used to assess the uterine cavity, endometrium, fibroids, polyps, scar tissue, congenital differences, and fallopian tubes.
An HSG can also help identify a hydrosalpinx (a fluid-filled, blocked fallopian tube).
Note: Not every fibroid, polyp, or uterine difference reduces the chance of IVF success. Size, location, and whether the finding distorts the uterine cavity help determine whether treatment is recommended.
7. Previous Pregnancy or Treatment History
Previous pregnancies, losses, IUI or IVF cycles, egg yield, fertilization, blastocyst development, embryo testing, and implantation history all provide clinically useful information.
An unsuccessful cycle does not mean the next cycle will have the same result. Your care team will review ovarian response, embryo development, and other findings to determine whether to change the medication, fertilization, or transfer plan.
8. Clinical Expertise & Laboratory Quality
IVF is a sequence of carefully coordinated clinical and laboratory steps, not one isolated procedure. Protocol selection, monitoring, trigger timing, egg retrieval, fertilization, embryo culture, cryopreservation, and transfer technique all require precision.
Clinical and laboratory expertise cannot change the biological age of the eggs, but it can reduce avoidable variation and help your team respond to what happens during your cycle.
9. Medical & Lifestyle Factors
General health affects treatment safety, reproductive function, and pregnancy outcomes. Your care team may discuss tobacco and nicotine use, medications, chronic conditions, nutrition, movement, sleep, mental health, and environmental exposures.
Smoking is one of the clearest modifiable reproductive risk factors and is associated with impaired fertility, pregnancy loss, and poorer IVF outcomes.
10. Body Weight & Metabolic Health
Body weight and metabolic health may influence ovulation, ovarian response, anesthesia risk, and pregnancy complications.
At Illume Fertility, patients must have a BMI below 45 before starting an IVF cycle and below 50 before starting an ovulation induction or IUI cycle. These clinic thresholds are intended to address anesthesia and medical risks.
If weight arises as a concern, our physicians and in-house nutrition team focus on safe, supportive preparation rather than extreme restriction or unsustainable measures.
What the Research Says
It's important to note that research on weight and fertility treatment outcomes is complex.
A 2026 study of 14,990 patients undergoing their first frozen transfer of a single euploid embryo found an association between obesity and a modest increase in early pregnancy loss. The study did not prove that weight caused those losses or show that losing weight before IVF would change the outcome.
Read our analysis of the research to learn what these findings can (and can't) tell us.
Current evidence does not show that delaying IVF solely for pre-treatment weight loss consistently improves live birth rates. ASRM recommends individualized, respectful counseling based on each patient’s complete health profile.
No single diet, supplement, or wellness practice can guarantee IVF success. That said, sustainable health habits can support treatment safety and preparation for pregnancy.
How PGT-A May Affect Embryo Selection
Preimplantation genetic testing for aneuploidy (PGT-A) screens a small sample of cells from the outer layer of a blastocyst for chromosome-number abnormalities. Human cells typically contain 46 chromosomes, arranged in 23 pairs.
A blastocyst is an early-stage embryo that usually develops about five to six days after fertilization. It has an inner cell mass, which develops into the fetus, and an outer layer called the trophectoderm, which contributes to the placenta.
PGT-A cannot create healthier embryos or correct chromosome abnormalities. It may help prioritize embryos for transfer in certain circumstances, but it is a screening test rather than a diagnostic test.
Mosaic or inconclusive results can be complex and may require consultation with a genetic counselor before decisions are made. At Illume Fertility, our in-house genetic counselors offer support and nondirective guidance to every patient navigating the PGT-A process.
Should I do PGT-A?
Not necessarily. Current ASRM guidance on PGT-A does not support routine testing for every IVF patient. The right decision for your family depends on age, the number of embryos available, reproductive history, and treatment goals.
Your care team can help review the possible benefits, limitations, risks, and costs.
Explore a Typical IVF Cycle
Download our Guide to IVF Treatment to learn about the process, from testing and medications to retrieval, embryo transfer, and what to expect along the way.

Preparing for Fertility Treatment
Some of the most influential factors, including egg age and reproductive history, cannot be changed. That can be difficult to accept in a culture that often implies the right food, supplement, or routine can control the outcome.
The truth is no diet, supplement, or routine can overcome every biological factor. However, there are some practical steps you can take to prepare for treatment:
- Complete the recommended fertility evaluation
- Avoid tobacco and nicotine
- Review medications and supplements with your clinicians
- Manage chronic conditions
- Follow treatment instructions carefully
Incorporating holistic support for nutrition, mental health, acupuncture, and other aspects of wellness can also make treatment feel more manageable.
While stress does not cause infertility or mean you're at fault for an unsuccessful cycle, fertility treatment can still create a substantial emotional burden. Illume's free events and support resources are designed to help every patient feel informed and connected throughout the family-building process.
Does everyone start with IVF?
No. Treatment recommendations depend on your diagnosis, age, and family-building goals.
For many patients with unexplained infertility, ASRM recommends a limited course of ovarian stimulation with oral medication and IUI before moving to IVF. Age, ovarian reserve, sperm parameters, treatment history, desired family size, and your timeline may support moving to IVF sooner.
Some insurance plans require a specific order or number of treatments before approving IVF coverage. Check your plan’s rules and ask your financial coordinator about any prerequisites.
What if your chances of success are lower?
As reproductive endocrinologists, one of the hardest conversations we have with patients often happens before any injections or pregnancy tests. It is the conversation where we have to explain that assisted reproductive technology is not a guarantee for anyone.
We cannot ethically promise you a baby. What we can promise is that our team will use the best available science, innovative technology, and creative problem-solving to give you the strongest reasonable chance of reaching your goals.
Don't Give Up Hope
A lower statistical probability is not the same as no possibility.
It does mean that you deserve honest counseling about the likelihood of retrieving eggs or creating embryos, the possibility that multiple cycles may be needed, the financial and emotional impact of continuing, and whether another family-building path could improve your outlook.
Options may include donor conception, or in some cases, a gestational surrogate. The goal is not to force hope or remove it. It is to give you enough information and support to make a decision that reflects your values, limits, and family-building goals.
When to Consult a Fertility Specialist
For opposite-sex couples having regular, unprotected intercourse without a known fertility concern, evaluation is recommended after 12 months when the partner providing eggs is younger than 35, after six months at age 35 or older, and more immediately after age 40.
You should seek help sooner if you have irregular or absent cycles, known or suspected endometriosis, PMOS (formerly PCOS), previous pelvic infection or surgery, blocked fallopian tubes, diminished ovarian reserve, a known sperm concern, recurrent pregnancy loss, a genetic condition, or a medical history that may affect fertility or pregnancy.
Note: You do not need to wait six or 12 months if you plan to use donor eggs, sperm, or embryos, you are pursuing parenthood without a partner, or you have an LGBTQ+ family-building plan that requires reproductive assistance.
ASRM's current definition of infertility recognizes these pathways and the need for medical intervention based on a person's reproductive circumstances.
Estimating Your Chances of IVF Success
Your reproductive endocrinologist can provide a personalized estimate after reviewing age at egg retrieval, ovarian reserve, semen analysis, uterine and tubal testing, diagnosis, pregnancy history, previous treatment outcomes, and whether donor eggs, sperm, or embryos are being used.
The CDC IVF Success Estimator and SART Patient Predictor can help estimate outcomes using data from patients with similar characteristics. These tools can be useful for planning, but they are still statistical models. They cannot account for every clinical detail or guarantee an individual result.
IVF Success Rate FAQs
What is the biggest predictor of IVF success?
Age at egg retrieval is one of the strongest predictors when using your own eggs. Embryo development, ovarian response, sperm quality, diagnosis, uterine health, and previous treatment history also matter.
Is IVF success measured per transfer or per retrieval?
It can be measured either way. A per-transfer rate includes only embryo transfers that took place. A per-retrieval or per-intended-retrieval rate includes more of the IVF process and usually gives a broader picture of the chance of having a baby after beginning treatment.
Does AMH predict whether IVF will work?
Not by itself. Anti-Müllerian hormone (AMH) is most useful for estimating ovarian reserve and predicting how the ovaries may respond to stimulation medication. It is not a direct test of egg quality and has only a weak relationship with pregnancy or live birth when considered independently.
Can you have successful IVF with low AMH?
Yes. Low AMH may mean fewer eggs are expected during retrieval, but it does not mean pregnancy is impossible. Age, antral follicle count, previous response, and the development of any embryos created provide additional information.
Does PGT-A increase IVF success?
Preimplantation genetic testing for aneuploidy (PGT-A) may help prioritize an embryo that is more likely to be chromosomally normal in certain circumstances, but it has not been shown to increase the overall live birth rate for every patient. Its value depends on age, embryo quantity, reproductive history, and individual goals.
How many IVF cycles does it usually take to have a baby?
There is no universal number. Some patients have a baby after one egg retrieval and embryo transfer, while others need multiple retrievals or transfers. Success can build across treatment cycles. SART data tracks cumulative live birth rates across complete IVF cycles.
Age at the time of egg retrieval is one of the strongest predictors of IVF success. Diagnosis, ovarian reserve, embryo development, embryo availability, and previous treatment outcomes also shape an individual patient's chances.
Are frozen embryo transfers more successful than fresh transfers?
Neither approach is more successful for every patient. A large randomized trial found similar live birth rates with fresh and frozen embryo transfer in many patients.
A frozen embryo transfer may be recommended when embryos undergo genetic testing, hormone levels or the uterine environment make a fresh transfer less favorable, or there is a higher risk of ovarian hyperstimulation syndrome (OHSS).
ASRM guidance supports freeze-only cycles for patients at increased risk of OHSS.
Does embryo grade predict IVF success?
Embryo grading provides useful information about appearance and development, but it cannot confirm chromosomal health or guarantee implantation. Egg age, developmental stage, chromosomal status, and individual clinical factors must also be considered.
Why do fertility clinics have different success rates?
Differences may reflect patient age, diagnoses, treatment methods, laboratory practices, cycle volume, and which patients a clinic accepts for treatment. Published rates should be interpreted in context rather than used as the only factor when choosing a fertility practice.
Is IUI or IVF more successful?
IVF generally has a higher chance of pregnancy per treatment cycle, but IUI may still be the right first treatment for patients with open fallopian tubes, sufficient sperm parameters, and certain diagnoses. The best choice depends on testing, age, timeline, cost, and family-size goals.
Can an IVF success calculator predict my outcome?
An IVF calculator provides an estimate based on outcomes among patients with similar characteristics. It cannot account for every detail of your health or predict exactly what will happen during treatment.
Finding Your Own Path Forward
Success rate data can help you ask more informed questions and understand the general possibilities of fertility treatment, but they should not be used to reduce your future to a single percentage.
Your outlook is shaped by your age, testing, diagnosis, reproductive history, treatment plan, and goals. Even patients within the same age group may receive very different recommendations or experience very different outcomes.
At Illume, our reproductive endocrinologists, embryologists, and support team review your case, explain your options, and develop a treatment plan around your family-building goals.
Ready to better understand your fertility and treatment options? Schedule an initial consultation to discuss your individual chances of success with fertility treatment.

Is IVF the right path for you?
Get personalized recommendations from our experts by taking a short assessment.


Considering IVF? We can help.
Our team of nine board-certified reproductive endocrinologists is ready to help you achieve your family-building dreams. Reach out to us today to get started!